Erasing unique accomplishments as DEI

If anyone is still inclined to think the government’s efforts to delete “DEI” hires are aimed at people hired for reasons other than their skills, consider the case of the Navajo Code Talkers. Pages about them have been removed from DOD websites and replaced with “DEI.”

These Americans had a unique skill that no one else possessed. Their ability to speak in Navajo during WWII created a code that no enemy ever broke. They enabled us to win critical battles during World War II. High-level military leaders said the Allies could not have won those battles without them.

And yet they’ve been cancelled. Erased. Told they were only hired because they looked different than the majority population in the US during WWII, before the civil rights movement even existed. They accomplished it all despite the prejudice against them.

Where are all the objections to “cancel culture” now? Crickets.

I am ashamed of the way our government is erasing genuine accomplishments by people who don’t look like them or fit their definition of warfighter.

I’ve chosen a conservative media site for the supporting news article to show this isn’t a deception by liberal media. The image on this blog comes from this article.

https://www.newsmax.com/amp/newsfront/navajo-codetalkers-dod/2025/03/17/id/1203224/

Amp up your lung cancer patient advocacy! Apply for the STARS Program

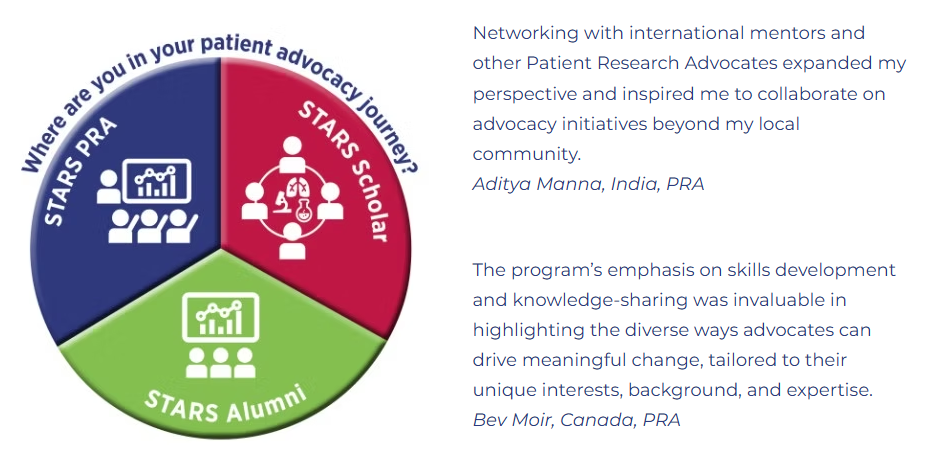
Take steps to amp up your lung cancer patient advocacy! Applications are now open for the 2025 IASLC STARS PRA & Scholar Programs. STARS (Supportive Training for Advocates on Research and Science) can help you develop and enhance research advocacy skills needed to provide a patient perspective to research.

If you or a loved one has been affected by lung cancer, and you are an active lung cancer patient advocate, you are eligible to apply. Learn more on the STARS website.

Why this cancer patient and advocate is walking away from X. (Hint: it’s not politics)

I’ve been living with and communicating about lung cancer for over 13 years. Since 2011 (the year I was diagnosed) I’ve been active in one or more online lung cancer patient groups. Since 2012, I’ve been blogging and on social media, connecting with the lung cancer community and learning/sharing developments in cancer research. In 2013, I cofounded #LCSM (lung cancer social media) Chat on Twitter and became a co-moderator of its weekly chats. As an active lung cancer patient research advocate, I’ve presented at national and international oncology conferences about using social media in the lung cancer community to improve education, clinical trials., and patient care.

Nowadays I spend most of my social media time in the private “ROS1 Positive (ROS1+) Cancer” Facebook group I cofounded (my ROS1+ cancer is a rarer form of lung cancer) and related online accounts. I know there are data security risks in sharing my cancer journey on public and private social media platforms, but it’s one of the most effective ways to reach other people who are living with lung cancer, especially for rarer subtypes.

All of that is to give you some background about my participation in social media. I’ve been very active online. I don’t sift through random posts about celebrities or debates about news events, but I have been known to spend hours online following developments in cancer research, posts from people attending oncology conferences, and discussions about cancer care from the patient perspective.

I used to do a lot of my research and outreach on Twitter. But due to evolving policies, algorithms, and accounts on X, I now spend almost no time on that platform. The Elon era substantially reduced its usefulness for this lung cancer patient advocate. I’ll try to explain why.

  1. While cancer social media has always had to contend with medical misinformation, it became significantly worse on X after moderation was cut back. I’ve also seen a dramatic increase in hateful comments, personal attacks, and anti-science sentiment. I don’t want to waste my time reading that stuff while trying to find the content I value.
  2. A blue checkmark on an account used to mean that account was owned by a validated organization, agency, or individual that had significant public impact. Patients could distinguish which accounts shared trusted, evidenced-based medical information . Now anyone can buy a blue checkmark, impersonate whoever they want, and spread medical disinformation that is not helpful or safe. While not all patients are successfully treated, the survival rate for lung cancer has increased significantly over the past decade. I’m not the only metastatic lung cancer patient who has survived for more than 10 years thanks to newer treatments like targeted therapies and immune checkpoint inhibitors. Yet I know people who died because they decided to forego an evidenced-based new cancer treatment in favor of some “cure” they found online that had only a few anonymous anecdotes to support it.
  3. When you blocked someone on Twitter, you could no longer see them and they could no longer see you. Now when you block someone on X for malicious behavior, they can still see your posts. I prefer to have more control over who sees my content.
  4. The platform terminated its free API (Application Programming Interface). This disrupted a lot of applications and websites that patient advocates and others used to interact with the platform and archive material from online chats. I have to spend more time to accomplish less.
  5. My X feed used to be filled with content from people I chose to follow. Now it’s filled with ads and people I never chose to follow that don’t interest me in the slightest. I can’t find the content I want, and those who follow me don’t see the content I generate. The only way I can find useful cancer-related content is by using hashtags like #lcsm, but even hashtag-curated content is greatly reduced because so many members of the cancer community have stopped posting on the platform.
  6. As of today, any content posted on X can be used to feed AI engines. While I’ve always known my posts on Twitter/X were publicly visible, it does bother me that the platform would deliberately hijack my content for their own uses without any acknowledgment or compensation.

So, there it is. I want to make a difference in the cancer space, and I have a limited amount of time and energy available to do it. Wading through uncurated content, hostile posts, and medical misinformation isn’t how I want to spend my days.

It’s sad to see the era of Twitter cancer communities end. Twitter was the one place where all stakeholders–patients, caregivers, advocates, clinicians, academic cancer centers, researchers, government agencies, industry, and the general public–could meet and exchange ideas on something that had life-and-death implications for so many (lung cancer is the #1 cancer killer). I hope someday another platform will attract enough participants to once again enable discussions across silos.

Reflections on November 6

Regardless of changes in
The players
Or game board
Or boundaries
Or rules

We each get to decide how to play the hand we’re dealt

Whether to find joy
To help others
To show kindness
To be a force for good
To adapt
To find a new path

Life may not look the same as it did yesterday
But the challenge remains the same:

How will YOU make a difference in whatever time you have?

A podcast in which I talk about the IASLC STARS Program

The International Association for the Study of Lung Cancer (IASLC) is celebrating its 50th Anniversary! As part of the #IASLC50 celebration, the Lung Cancer Considered podcast takes a look at the past, present & future of the organization. In this episode, host @StephenVLiu focuses on the IASLC today and some of the ongoing efforts of the IASLC & its members. W/@ChristianRolfo, @JFreemanDaily & Dr. Emily Stone: https://bit.ly/LCC50IASLC#LCSM

For more information about the IASLC STARS program, visit iaslc-stars.org.

How Is Artificial Intelligence used in Cancer Research?

There’s still time to register for the STARS Webinar on “Advancing Trustworthy Artificial Intelligence for Cancer Research.” Hope you’ll join us tomorrow, Thursday, August 29 at 3 pm MDT (Denver time). Once you register, the Zoom link will be emailed to you.

https://www.iaslc.org/meetings-webinars/advancing-trustworthy-artificial-intelligence-cancer-research

Why don’t people trust medical science?

I’ve been thinking about why some people don’t trust medical science and doctors in the US (and, increasingly, globally).

I’m not talking about issues with the medical system like ethical lapses, insurance snafus, cost, poor communications, malpractice, politicization, etc. I want to talk about issues with science.

I think a major source of distrust in medical science lies in the fact that no two human bodies are exactly alike–not even two identical twins. Stay with me on this one–it takes a while to explain.

For some medical procedures, like setting a broken bone, results are pretty predictable for the vast majority of people. However, when it comes to more complicated health issues like cancer and viruses, it’s less certain that medical science can generate specific results due to variations in the human body, nuances in the disease, and the fact that we don’t know everything about how the body or the disease works. (I’ve got 13 years as a cancer patient to support me on this).

The scientific process of discovery is the same in all areas of science, but the level of evidence available and predictability of results can vary depending on what’s being studied. In the engineering world where I was trained, once a physical law (e.g., the behavior of gravity on earth) has been confirmed by many observers, one can rely on it to remain true–at least until new data suggests the law may need to be revised.

The same is not true in medical science.

In medical science (particularly in drug development), a response to treatment in one person does not guarantee the same response will occur in another person who has the same condition. A person’s response can vary due to differences in the body, the environment, other health issues, or even the treatment process. This is why anecdotal evidence is not considered reliable evidence in medical science (although an individual response might indicate something is worth studying). A treatment must produce a similar response in many people to be considered effective–and even then, it may be effective only in people with certain characteristics. Based on decades of cancer research and treatment, claims of “This cancer treatment is guaranteed to work for EVERYBODY!” should generate significant skepticism.

If a hundred studies in engineering produce the same result, we trust the result will be true for all future studies. However, if a medical treatment is effective for 100 people, it still might not be effective for the 101st person. In the case of viruses (which mutate and may have as yet unknown effects on the body), medical evidence can tell you whether a vaccine can reduce your risk of getting infected/sick/dying from the virus, but it’s rare to get exactly the same results for all people.

People want science to be absolutely true, like engineering. When you turn on your stove, you trust it will generate heat for cooking. If it doesn’t work, it’s the machine’s fault, not the science.

But in medicine, the thinking is different. “The doctor said this treatment could keep me from getting sick. I still got sick. The treatment didn’t work, the doctor doesn’t know what they are talking about, the science is bad.”

Perhaps the lack of certainty makes medical science untrustworthy to some. And therefore “science” itself is bad.

How to fix this? Still thinking on that.

I’m a panelist for an FDA “Conversations on Cancer “!

Tomorrow (January 10, 2024) I will speak on an FDA panel as one of the patient advocates, along with clinical investigators and oncologists. The discussion will highlight transformative oncology drug approvals in 2023 including one for ROS1+ cancer (my type of cancer).

Topics we will discuss include patient and investigator perspectives on their experiences with these drugs, impact on patient’s prognosis and quality of life, how these drugs will change the treatment landscape, and barriers to access.

Hope you will tune in! You can register at: https://www.surveymonkey.com/r/FTYFN3H

FDA plans to post archived webcast of this Conversations on Cancer program at: https://www.fda.gov/about-fda/project-community/conversations-cancer

Edit to add 13-Jan-2024: The video is now available at https://www.youtube.com/watch?v=LSySqh2z-_A

Help The ROS1ders fund more research into ROS1+ Cancer!

Help me celebrate ELEVEN years of effective ROS1+ cancer targeted therapy by donating to The ROS1ders nonprofit through the Paypal Giving Fund ( NO ADDED FEES):
https://www.paypal.com/donate/?hosted_button_id=DH4CD2W3QQUKC

The backstory:

In May 2011 I was diagnosed with advanced lung cancer. At that time, surgery, chemo and radiation were the only treatments available. However, a small clinical trial had already begun for a targeted therapy pill called crizotinib. This pill that sounded like an alien seemed to inhibit ROS1+ cancer in about 80% of people in the trial. That was amazingly effective for a cancer drug!

I joined that trial, and as of yesterday, I’ve been on crizotinib for 11 years. Yes, I’m an outlier. While this drug has worked well for me, current targeted therapies don’t work well for everyone, and most people eventually develop resistance. We need more research and treatment options.

The ROS1ders (a nonprofit I cofounded) is funding research into ROS1+ cancers so all patients can one day have great treatment outcomes. This year we funded two $75,000 ROS1+ Cancer Innovation Awards. We are aiming to raise $225,000 so next year we can fund three awards.

I’m in Boston today, where I spoke to a pharmaceutical company that has new ROS1 drug in clinical trials, and met with a researcher who will be starting a new study about my type of cancer. Please help me fund more research to find better treatments for my rare type of lung cancer. Thanks for your support!

Register for an IASLC STARS Webinar on October 30!

The IASLC STARS (Supportive Training for Advocates on Research and Science) webinar will include a sampling of patient advocate research abstracts presented at the 2023 IASLC World Conference on Lung Cancer (WCLC23) in Singapore. A live Q&A session will follow, moderated by lung cancer patient and research advocate Janet Freeman-Daily. The speakers are Mentors for the 2023 IASLC STARS program:

• Upal Basu Roy, PhD, MPH, Executive Director of Research at LUNGevity Foundation
• Andrew Ciupek, PhD, Associate Director of Clinical Research at GO2 for Lung Cancer
• Jill Feldman, MS, lung cancer patient and research advocate
• Anne-Marie Baird, PhD, president of Lung Cancer Europe (LuCE)
• Lillian Leigh, JD, lung cancer patient and policy advocate

Educational Objectives:

  1. Highlight range of research conducted by lung cancer research advocates and advocacy organizations. 
  2. Demonstrate effective communication of research topics to a broad audience. 
  3. Increase patient research advocates’ understanding of research abstract format and content presented at conferences.
  4. Raise awareness of research advocates contributions to improving patient care and outcomes. 

Live interpretation will be offered in these languages:

  • Chinese (Mandarin)
  • French
  • German
  • Greek
  • Japanese
  • Spanish (Latin America/neutral)

The webinar will be recorded and available for viewing afterwards in each offered language.

Please reach out to advocacy@iaslc.org with any questions.

REGISTER HERE!
https://www.iaslc.org/meetings-webinars/wclc23-you-presented-lung-cancer-research-advocates